


Parathyroid hormone–related protein–mediated hypercalcemia of malignancy: insights from a multicenter clinical data warehouse
-
Jinyoung Kim1, Yuri Shin2, Jeonghoon Ha3, Chaiho Jeong4, Jeongmin Lee5, Kwanhoon Jo6, Jang Won Son7, Jae-Seung Yun8, Ihnsuk Lee9, Dong-Jun Lim3, Hyuk-Sang Kwon1, Ki-Ho Song1, Ki-Hyun Baek1

- Received February 24, 2026; Revised April 27, 2026; Accepted May 11, 2026;
- Abstract
-
- Background/Aims
- Parathyroid hormone–related protein (PTHrP) is a major mediator of hypercalcemia in patients with malignancy; however, understanding of PTHrP-mediated hypercalcemia remains limited because available evidence has largely been derived from small case series.
- Methods
- We retrospectively analyzed electronic medical records from eight hospitals affiliated with The Catholic University of Korea. Adult patients (> 20 years) with confirmed malignancy and albumin-corrected hypercalcemia (≥ 10.5 mg/dL) between 2013 and 2022 were identified and classified as having PTHrP-mediated hypercalcemia (PTHrP > 1.1 pmol/L) or hypercalcemia due to other causes (PTHrP ≤ 1.1 pmol/L).
- Results
- Among the 289 patients reported to have PTHrP-mediated hypercalcemia, median age was 66 years (interquartile range [IQR], 59–75) and median plasma PTHrP level was 6.1 pmol/L (IQR, 3.5–11.5). Solid tumors accounted for 86% of cases, while hematologic malignancies accounted for the other 14%. The most common cancer types were lung cancer (30%, n = 87), head and neck cancer (11%, n = 31), and multiple myeloma (8%, n = 24). Median survival after the onset of hypercalcemia was 46 days (95% confidence interval [CI], 36–61) in patients with PTHrP-mediated hypercalcemia. Compared with the 169 patients with hypercalcemia due to other causes, PTHrP-mediated hypercalcemia was associated with a higher risk of mortality after adjustment for age, corrected calcium level, and cancer type (adjusted hazard ratio, 4.0; 95% CI, 2.9–5.4).
- Conclusions
- PTHrP-mediated hypercalcemia occurs across a broad spectrum of malignancies and is associated with worse clinical outcomes.
- Graphical abstract
- Graphical abstract
- INTRODUCTION
- INTRODUCTION
Hypercalcemia is among the most common metabolic complications of malignancy, occurring in approximately 3–30% of patients with cancer during the course of their disease [1,2]. Parathyroid hormone–related protein (PTHrP) was first suggested as a mediator of humoral hypercalcemia of malignancy in 1941 based on a case of squamous cell carcinoma of the lung [3]. Measurement of PTHrP became feasible after its molecular characterization in 1987 [4].PTHrP comprises a family of protein isoforms ranging from 60 to 173 amino acids, sharing an N-terminal sequence and biological activity similar to that of parathyroid hormone (PTH) [5]. PTHrP acts on the same target organ receptors as PTH and induces hypercalcemia by enhancing bone resorption and renal tubular calcium reabsorption [6]. Currently, PTHrP is considered responsible for more than 80% of cases of cancer-related hypercalcemia [7].Unlike PTH, which is produced exclusively in the parathyroid glands, PTHrP is widely expressed in normal tissues, including bone, stomach, pancreas, cardiovascular and renal systems, lung, and mammary gland [8]. Therefore, in malignancy, elevated PTHrP levels are thought to be closely related to the growth of the primary tumor and metastatic progression. This study aimed to clarify the clinical features of PTHrP-mediated hypercalcemia in patients with malignancy.
- METHODS
- METHODS
- Data source
- Data source
The data source for this study was a data platform for research purposes created based on electronic medical records from eight hospitals affiliated with the Catholic University of Korea. Through screening of laboratory results obtained between 2013 and 2022, cancer patients aged > 20 years who underwent PTHrP measurement were identified. Among these, patients with elevated albumin-corrected serum calcium (≥ 10.5 mg/dL) were included in the analytic cohort and subsequently classified into the PTHrP-mediated hypercalcemia group (PTHrP > 1.1 pmol/L) or the other causes group (PTHrP ≤ 1.1 pmol/L) (Fig. 1). The study protocol was reviewed and approved by the Institutional Review Board of Yeouido St. Mary’s Hospital (IRB No. SC24WIDE0011).- Laboratory assays
- Laboratory assays
Serum PTHrP levels were measured at a central laboratory using a two-site immunoradiometric assay (Mitsubishi Kagaku Iatron Inc., Tokyo, Japan). This assay targets both the N-terminal and C-terminal regions of PTHrP and is capable of detecting multiple isoforms, including PTHrP (1–87), (1–95), (1–108), and (1–141). Importantly, the assay has been reported not to cross-react with serum PTH.Serum PTH and creatinine levels were obtained from measurements performed at our institution. Estimated glomerular filtration rate (eGFR) was calculated using the 2021 Chronic Kidney Disease Epidemiology Collaboration (CKDEPI) creatinine equation incorporating age and sex. Chronic kidney disease (CKD) was defined as stage 4–5 CKD (eGFR < 30 mL/min/1.73 m2) or ongoing renal replacement therapy.- Statistical analysis
- Statistical analysis
Continuous variables are presented as medians [interquartile range], and categorical variables as numbers (%). Comparisons between groups were performed using the Mann–Whitney U-test for non-normally distributed continuous variables and the chi-square test or Fisher’s exact test for categorical variables, as appropriate. To evaluate prognosis, survival analyses were performed using Kaplan–Meier curves and Cox proportional hazards regression. Statistical analyses were performed with R version 4.3.1 program (R Foundation for Statistical Computing, Vienna, Austria).
- RESULTS
- RESULTS
- Baseline characteristics
- Baseline characteristics
PTHrP-mediated hypercalcemia accounted for 63% (289/458) of all cases of hypercalcemia in patients with malignancy. Median age was 66 years in both the PTHrP-mediated and other causes cohorts. In patients with PTHrP-mediated hypercalcemia, median PTHrP level was 6.1 pmol/L (interquartile range, 3.5–11.5) and did not differ significantly according to renal function (non-CKD: 6.1 [3.8–11.4] pmol/L; CKD: 4.9 [1.8–18.8] pmol/L; p = 0.248). Patients with PTHrP-mediated hypercalcemia had significantly higher calcium levels and lower phosphorus levels than those with hypercalcemia due to other causes, while this latter group had higher PTH levels and poorer renal function (Table 1). There were several patients in the other causes group with preserved kidney function who showed markedly elevated PTH levels (> 1.5-fold above the upper reference limit), and this finding was not limited to the two cases of parathyroid cancer (Supplementary Table 1).- Cancer type distribution
- Cancer type distribution
Among the 289 patients with PTHrP-mediated hypercalcemia, 86% (n = 248) had solid cancers and 14% (n = 41) had hematologic malignancies. The most common cancer types were lung cancer (30%, n = 87), head and neck cancer (11%, n = 31), and multiple myeloma (8%, n = 24). In the other causes hypercalcemia group, the proportion of hematologic malignancies was higher, accounting for 39% of cases (Table 2).- Survival analysis
- Survival analysis
In the PTHrP-mediated hypercalcemia group, 211 of 289 patients died, with a median survival of 46 days (95% confidence interval [CI], 36–61), whereas median survival was not reached in the other causes group (log-rank p < 0.001; Fig. 2). In sequential Cox regression analyses, elevated PTHrP was consistently associated with increased mortality across all models. After adjustment for age, albumin-corrected serum calcium, and cancer type, elevated PTHrP remained an independent predictor of death (Table 3). Within the PTHrP-mediated hypercalcemia group, age, serum PTHrP level, corrected serum calcium level, and cancer type were all associated with survival (Fig. 3).
- DISCUSSION
- DISCUSSION
PTHrP-mediated hypercalcemia is now a well-recognized complication of malignancy; however, PTHrP exists in multiple isoforms, and the biological and clinical significance of these isoforms have not been fully elucidated [9]. To our knowledge, this case series represents the largest cohort reported to date of patients with PTHrP-mediated hypercalcemia. Furthermore, by demonstrating significant associations between serum calcium, PTHrP levels, and survival duration―relationships that were not clearly established in prior small-scale studies―our findings provide more robust evidence linking PTHrP activity to disease progression and prognosis in malignancy.PTHrP exerts biological effects similar to those of PTH through activation of the PTH1 receptor, leading to increased bone resorption and renal calcium reabsorption, along with enhanced renal phosphate excretion, ultimately resulting in hypercalcemia and hypophosphatemia [10]. Measurement of PTHrP is not routinely available using standard laboratory assays, and even in tertiary referral centers in Korea, PTHrP testing is often outsourced to specialized laboratories in Japan. Therefore, in patients with hypercalcemia who exhibit normal or decreased serum phosphate levels in the presence of suppressed or inappropriately low PTH concentrations, PTHrP-mediated hypercalcemia should be considered.However, interpretation of serum phosphate levels requires caution, as the phosphaturic effect of PTHrP may be attenuated in patients with impaired renal function. Although phosphorus levels showed a low-normal pattern in the overall PTHrP-mediated hypercalcemia group, this pattern was not evident in patients with impaired renal function, in whom phosphorus levels were within or above the reference range (Table 1). Interpretation of absolute PTHrP levels may also be more challenging in patients with impaired renal function, as C-terminal PTHrP can be falsely elevated in patients with CKD [11]. The assay used in the present study detects both C-terminal and N-terminal regions. In our cohort, PTHrP levels did not differ significantly between patients with and without CKD, and the proportion of patients with CKD tended to be higher in the comparator group without elevated PTHrP. These findings suggest that the assay used in this study was not substantially influenced by renal function.Tumor cells can upregulate PTHrP expression through multiple mechanisms related to malignant transformation and tumor progression. Activation of oncogenic signaling pathways, including rat sarcoma virus–mitogen-activated protein kinase (RAS–MAPK), transforming growth factor-beta (TGF-β), and Hedgehog pathways, has been shown to directly enhance PTHrP transcription in various cancer types [12]. Hypoxic conditions—an established hallmark of aggressive and invasive tumors—also induce PTHrP expression via hypoxia-inducible factor (HIF)–dependent pathways [13]. Tumors with bone metastases, or those interacting closely with the bone microenvironment, may further amplify PTHrP production through reciprocal signaling between tumor cells and osteoblast-lineage cells [14]. Moreover, unlike physiological PTH, tumor-derived PTHrP acts locally without regulation by systemic endocrine feedback loops. In other words, PTHrP functions in autocrine and paracrine manners, promoting tumor cell survival, proliferation, and invasion [15]. Taken together, this dysregulated local overproduction of PTHrP is thought to contribute to tumor progression and the development of humoral hypercalcemia of malignancy.In addition, the relatively frequent occurrence of PTHrP-mediated paraneoplastic syndromes in lung squamous cell carcinoma, as well as in head and neck and esophageal cancers, which are predominantly composed of squamous cell types, suggests a potential link to the intrinsic biological characteristics of squamous epithelial cells [16]. PTHrP is physiologically expressed in normal squamous epithelium and involved in epithelial cell proliferation and differentiation; thus, dysregulation of lineage-specific differentiation programs in squamous cell carcinoma may create a transcriptionally permissive environment for PTHrP overexpression. Notably, the epidermal growth factor receptor (EGFR)–MAPK/extracellular signal-regulated kinase (ERK) pathway, a central oncogenic driver in squamous malignancies, may further induce PTHrP expression, providing a biologically plausible explanation for the high prevalence of PTHrP-mediated hypercalcemia in advanced squamous tumors [17].In our cohort, PTHrP-mediated hypercalcemia accounted for 63% (289/458) of malignancy-associated hypercalcemia, lower than the 70–80% reported in the literature [18]. Previous case series have shown that elevated PTHrP levels occur across a broad spectrum of malignancies beyond lung cancer, with solid tumors accounting for approximately 70–80% of cases and hematologic malignancies for 20–30% [19,20]. Our findings are consistent with this pattern. A Korean cohort further demonstrated a relatively high prevalence of this complication in hepatobiliary cancers, including liver cancer, in contrast to Western cohorts; this difference was partly attributed to geographic differences in cancer incidence [21]. The liver and biliary tract are well recognized sites of paraneoplastic hormone production, reflecting their roles in protein synthesis, metabolic regulation, and developmental plasticity. Accordingly, PTHrP expression in hepatobiliary malignancies may result from cellular dedifferentiation and nonspecific ectopic hormone production rather than activation of a canonical squamous epithelial program [22].Moreover, in addition to cancer types in which this condition is well recognized, our analysis further demonstrated a substantial number of PTHrP-mediated hypercalcemia cases among patients with multiple myeloma [22]. Osteolytic bone lesions are a characteristic feature of multiple myeloma, and macrophage inflammatory protein-1α (MIP-1α), produced by malignant plasma cells within the bone marrow, has been implicated in cytokine-mediated osteolysis [23]. Notably, previous reports have described cases of hypercalcemia in patients with multiple myeloma in whom both PTHrP and MIP-1α levels were elevated, suggesting the concurrent contribution of PTHrP-mediated humoral hypercalcemia of malignancy and MIP-1α–driven local osteolysis [24]. In addition, a previous study suggested that multiple myeloma plasma cells can directly produce PTHrP, which acts in multiple functional fragment forms to support tumor cell survival and promote the progression of bone disease. In particular, PTHrP has been hypothesized to sustain myeloma cell survival and proliferation through intracrine mechanisms, while simultaneously enhancing osteoclast activation and the development of osteolytic lesions [25].With regard to prognosis, survival among patients with solid malignancies after the development of humoral hypercalcemia of malignancy is generally less than two months, and this rare condition has therefore been regarded as a predictor of poor survival [19,20,26]. In this multicenter cohort, elevated PTHrP levels were not merely associated with biochemical hypercalcemia but also demonstrated a graded relationship with clinical outcomes, suggesting that PTHrP activity may capture aspects of tumor burden, skeletal involvement, and systemic metabolic stress. Notably, the substantial proportion of hematologic malignancies observed in our cohort supports the concept that disruption of the bone microenvironment—characterized by enhanced osteoclast activation, cytokine-rich signaling, and hypoxia—may promote PTHrP expression even in cancers not classically associated with paraneoplastic endocrine syndromes. From an endocrine perspective, these findings imply that PTHrP should not be viewed solely as an epiphenomenon of malignancy, but rather as a dynamic hormonal signal that integrates pathological interactions among the tumor, bone, and kidney in advanced disease. Such a framework may help explain the heterogeneity of clinical presentations and underscores the potential value of PTHrP as a biologically informative biomarker, rather than a binary diagnostic marker, in patients with malignancy-associated hypercalcemia.This study has several limitations. First, due to its retrospective design, important clinical variables such as performance status and treatment status were not available for comprehensive evaluation, making it difficult to interpret the association between PTHrP levels and mortality as definitive evidence of an independent prognostic effect. Second, for additional clinical comparison, patients with malignancy-associated hypercalcemia without elevated PTHrP levels were also evaluated. However, direct matched comparisons between patients with similar disease stage were limited because of heterogeneity in tumor types and treatment strategies. Finally, while PTHrP elevation and associated hypercalcemia have been reported in certain benign conditions, such as heart failure [27], the present study was restricted to patients with advanced malignancies, and additional evaluations of other potential clinical conditions were not conducted.In conclusion, PTHrP-mediated hypercalcemia can arise during the progression of diverse malignancies and often reflects advanced disease and poorer outcomes. These observations emphasize the necessity for greater clinical vigilance and timely identification of this aggressive paraneoplastic condition.
- KEY MESSAGE
- KEY MESSAGE
1. PTHrP-mediated hypercalcemia is an important endocrine cause of severe hypercalcemia in patients with malignancy.2. PTHrP-related hypercalcemia is observed across a broad range of cancer types and is associated with extremely poor survival outcomes.3. PTHrP excess should be suspected in patients with cancer who present with hypercalcemia and suppressed parathyroid hormone levels to enable timely diagnosis and appropriate management.
Supplementary Information
Supplementary Information
- Notes
- Notes
-
Acknowledgments A portion of this study was presented in abstract form at the 2024 Fall Conference of Korean Endocrine Association in Daegu, Korea.
- Notes
- Notes
-
CRedit authorship contributions Jinyoung Kim: conceptualization, investigation, writing - original draft; Yuri Shin: investigation, data curation; Jeonghoon Ha: resources, investigation; Chaiho Jeong: resources, investigation; Jeongmin Lee: resources, investigation; Kwanhoon Jo: resources, investigation; Jang Won Son: resources, investigation; Jae-Seung Yun: resources, investigation; Ihnsuk Lee: resources, investigation; Dong-Jun Lim: investigation, writing - review & editing; Hyuk-Sang Kwon: resources, investigation; Ki-Ho Song: resources, investigation; Ki-Hyun Baek: conceptualization, investigation, supervision
- Conflicts of Interest
- Conflicts of Interest
-
Conflicts of interest The authors disclose no conflicts.
- Notes
- Notes
-
Funding None
Data availability statement
Data availability statement
The datasets generated and/or analyzed during the current study are not publicly available due to restrictions related to patient privacy and institutional review board approval but are available from the corresponding author upon reasonable request.
Figure 1
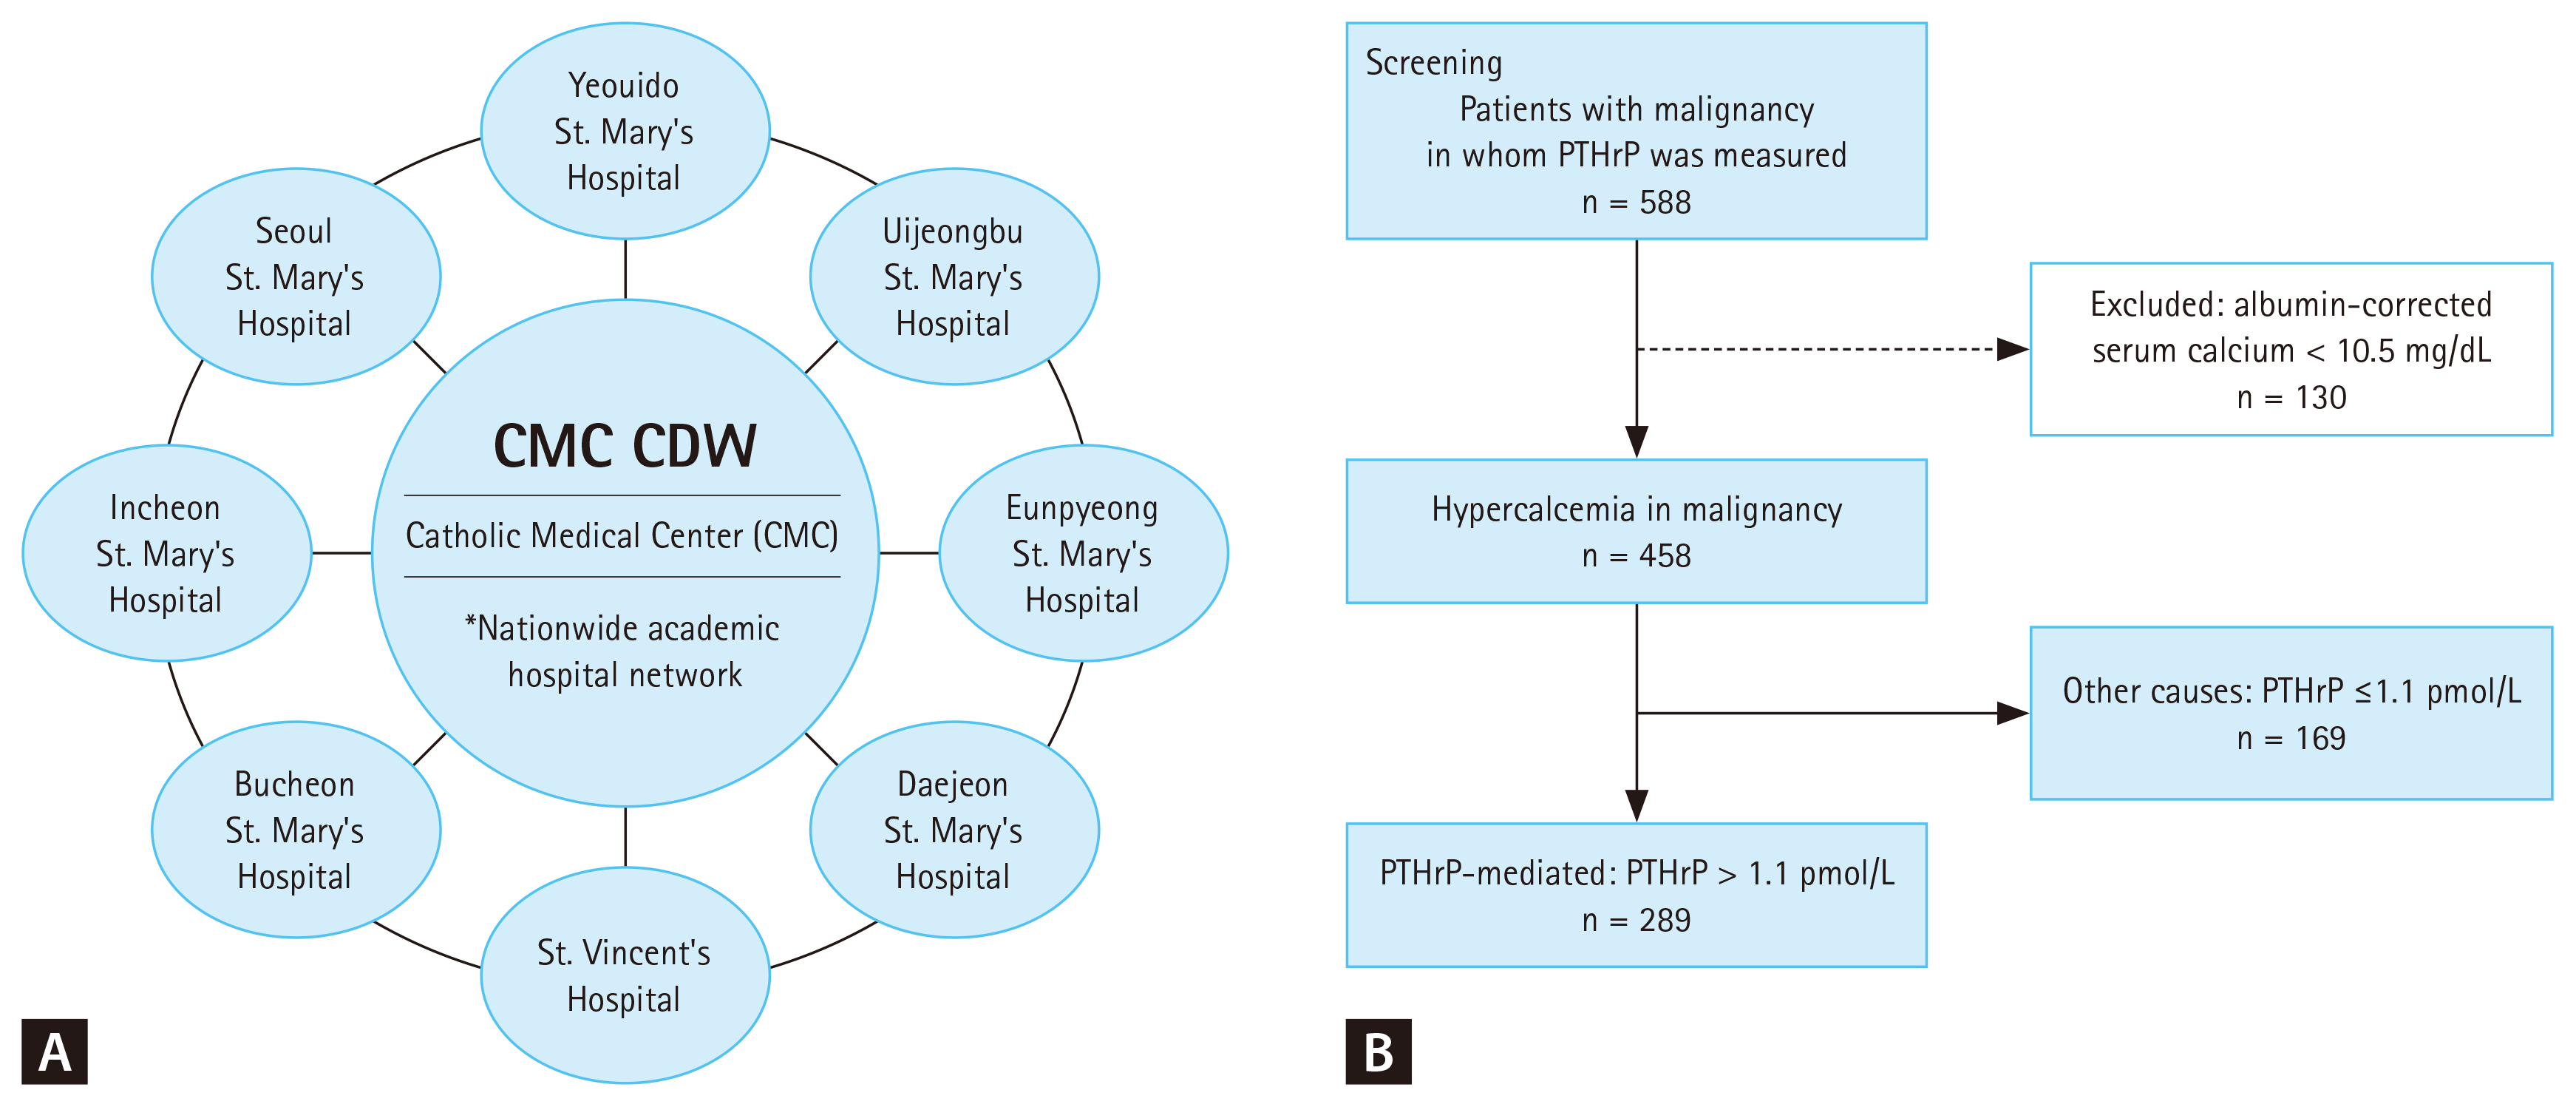
Figure 2
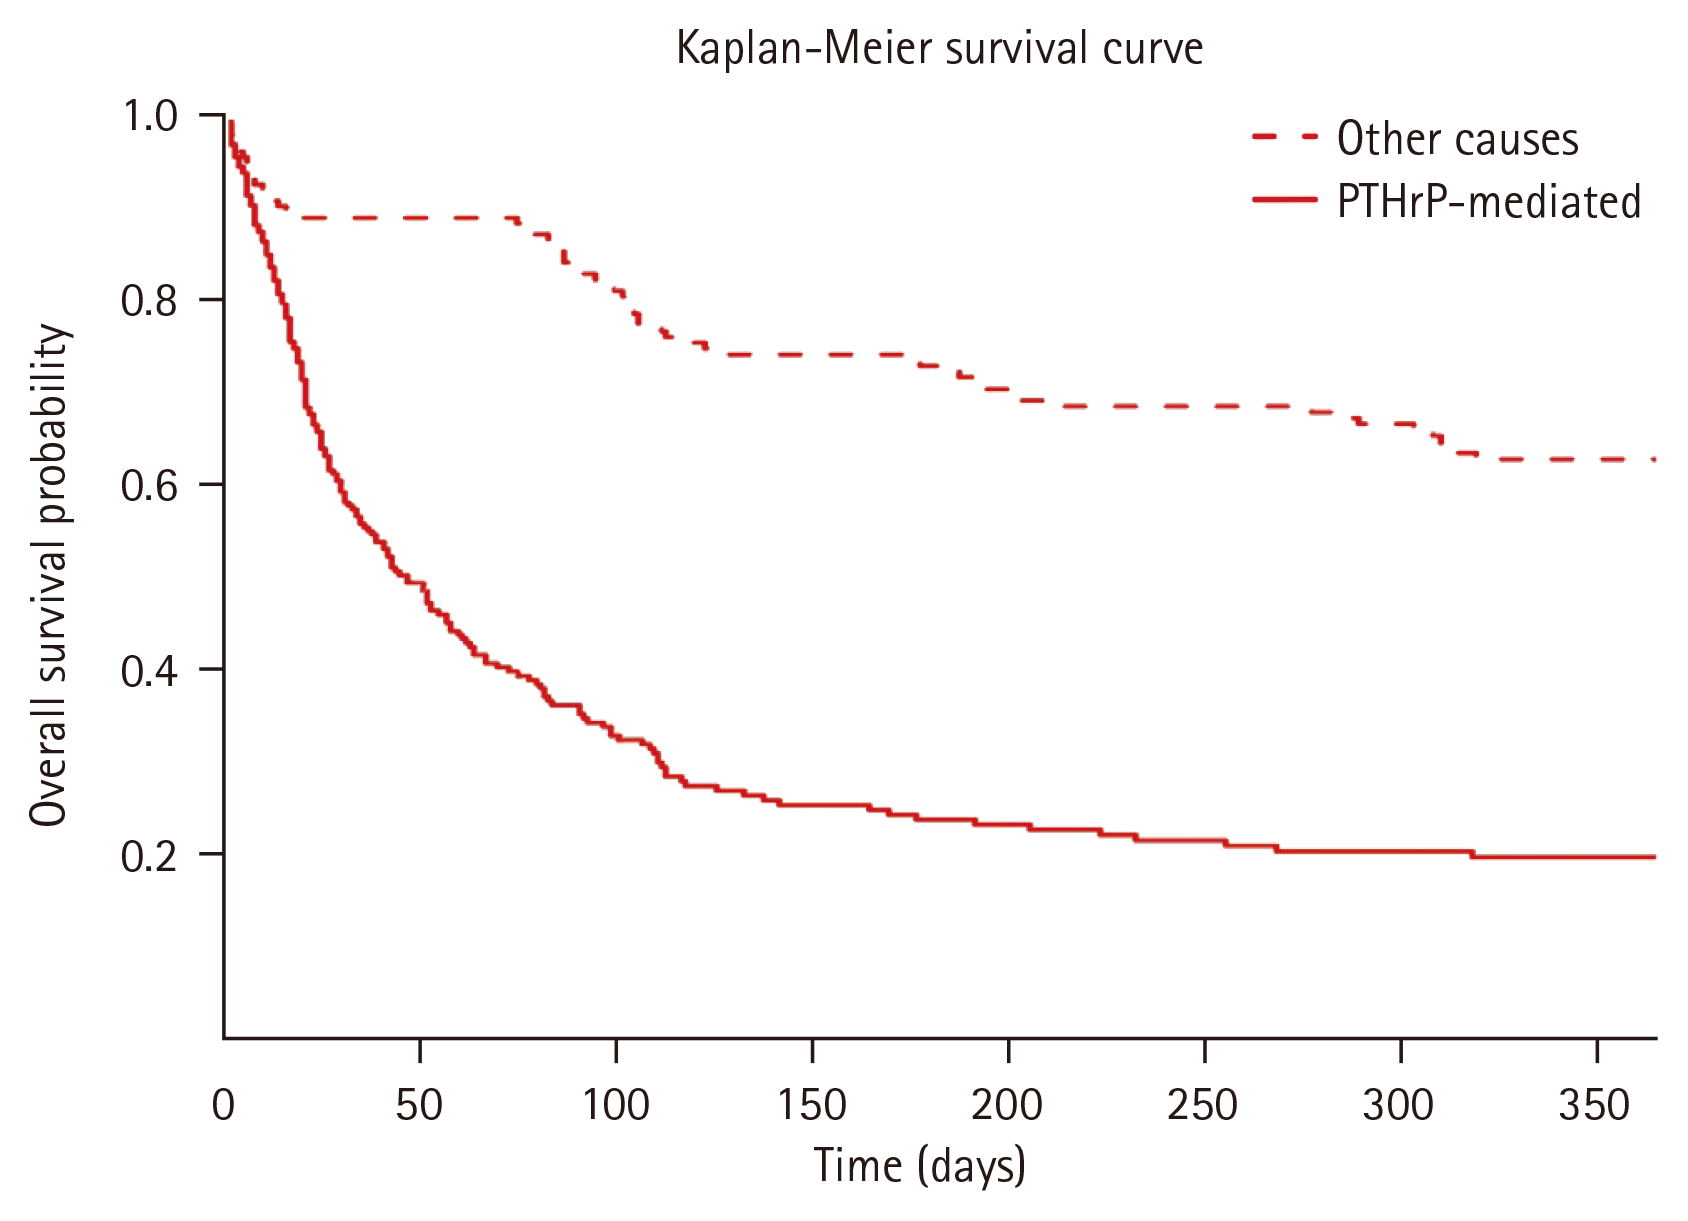
Figure 3
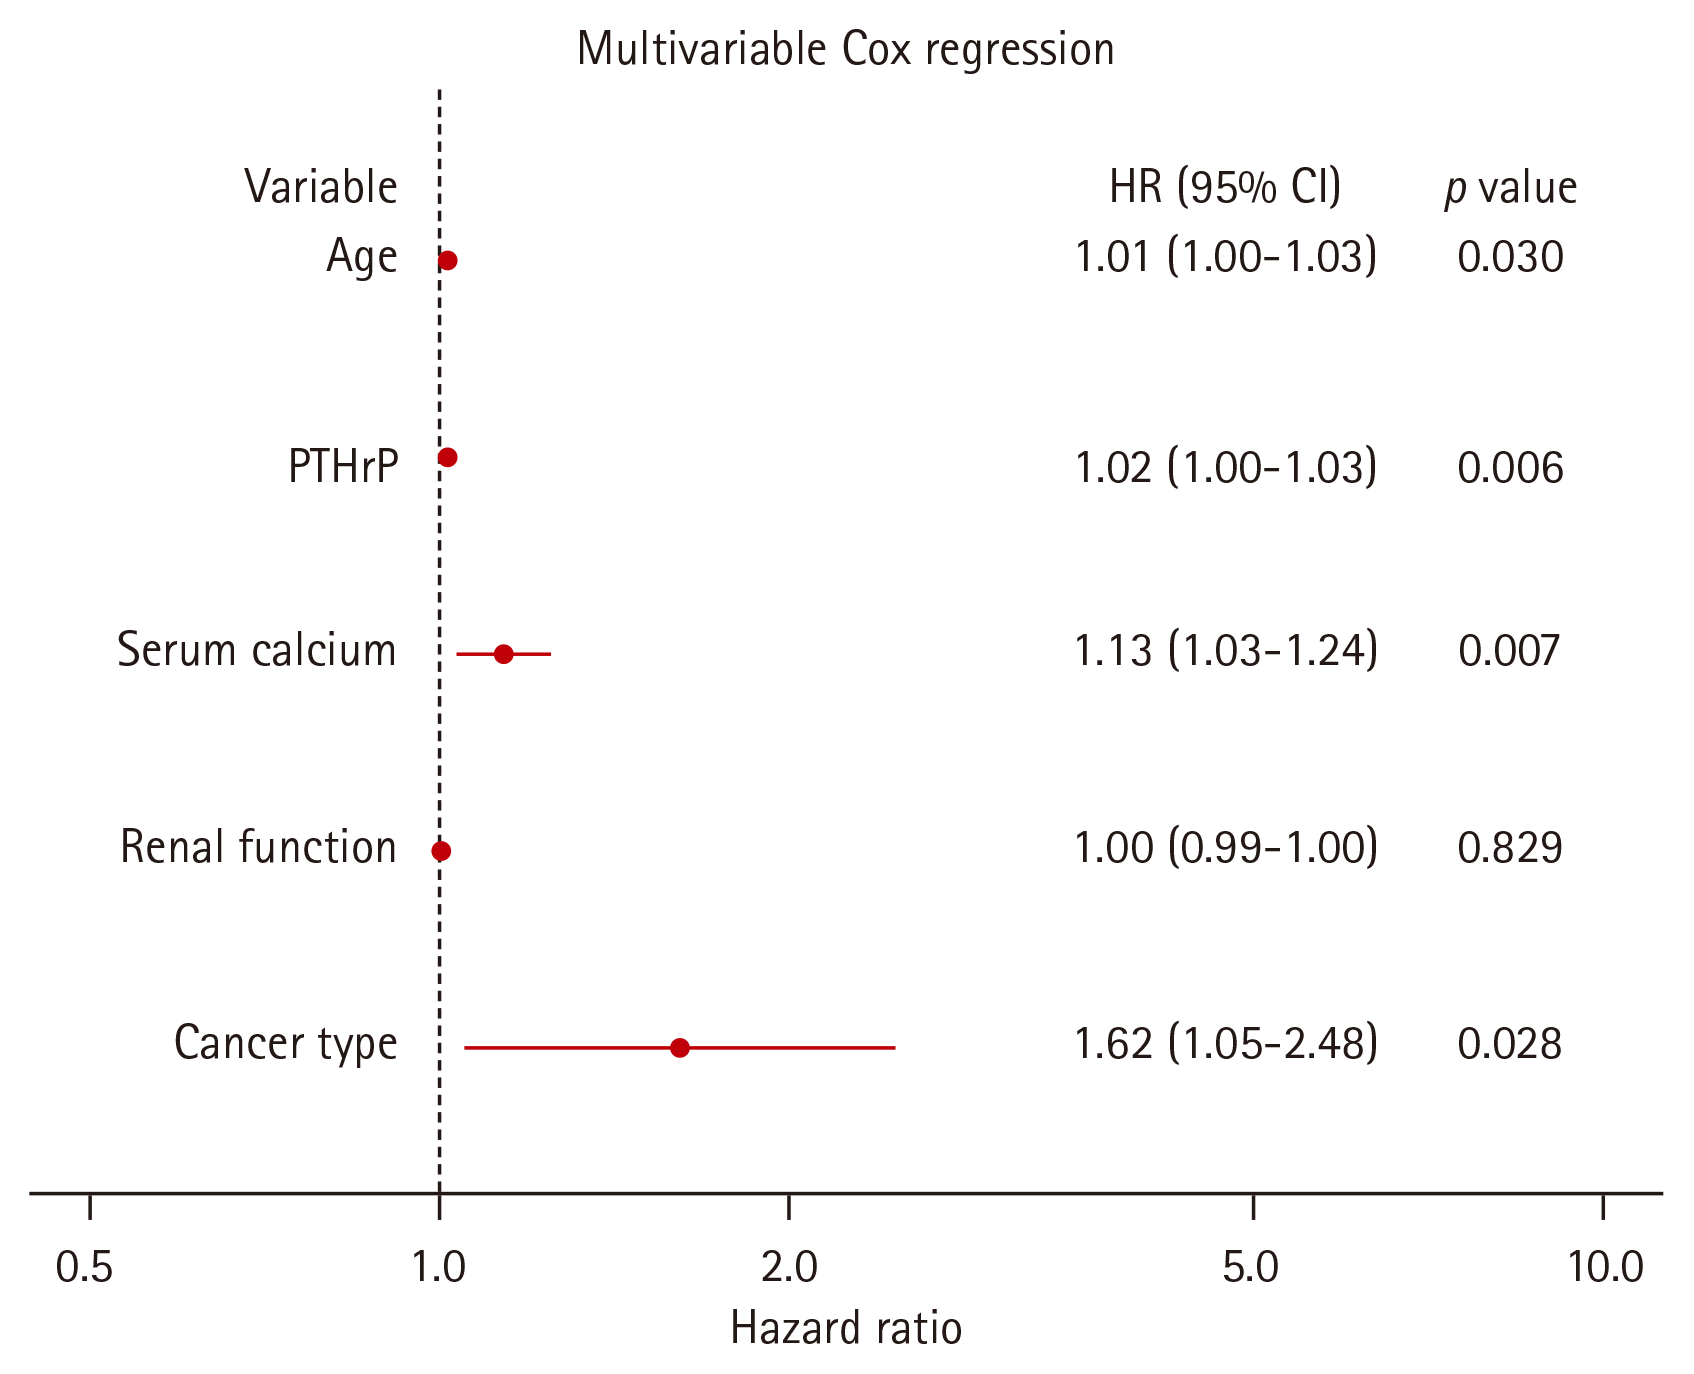
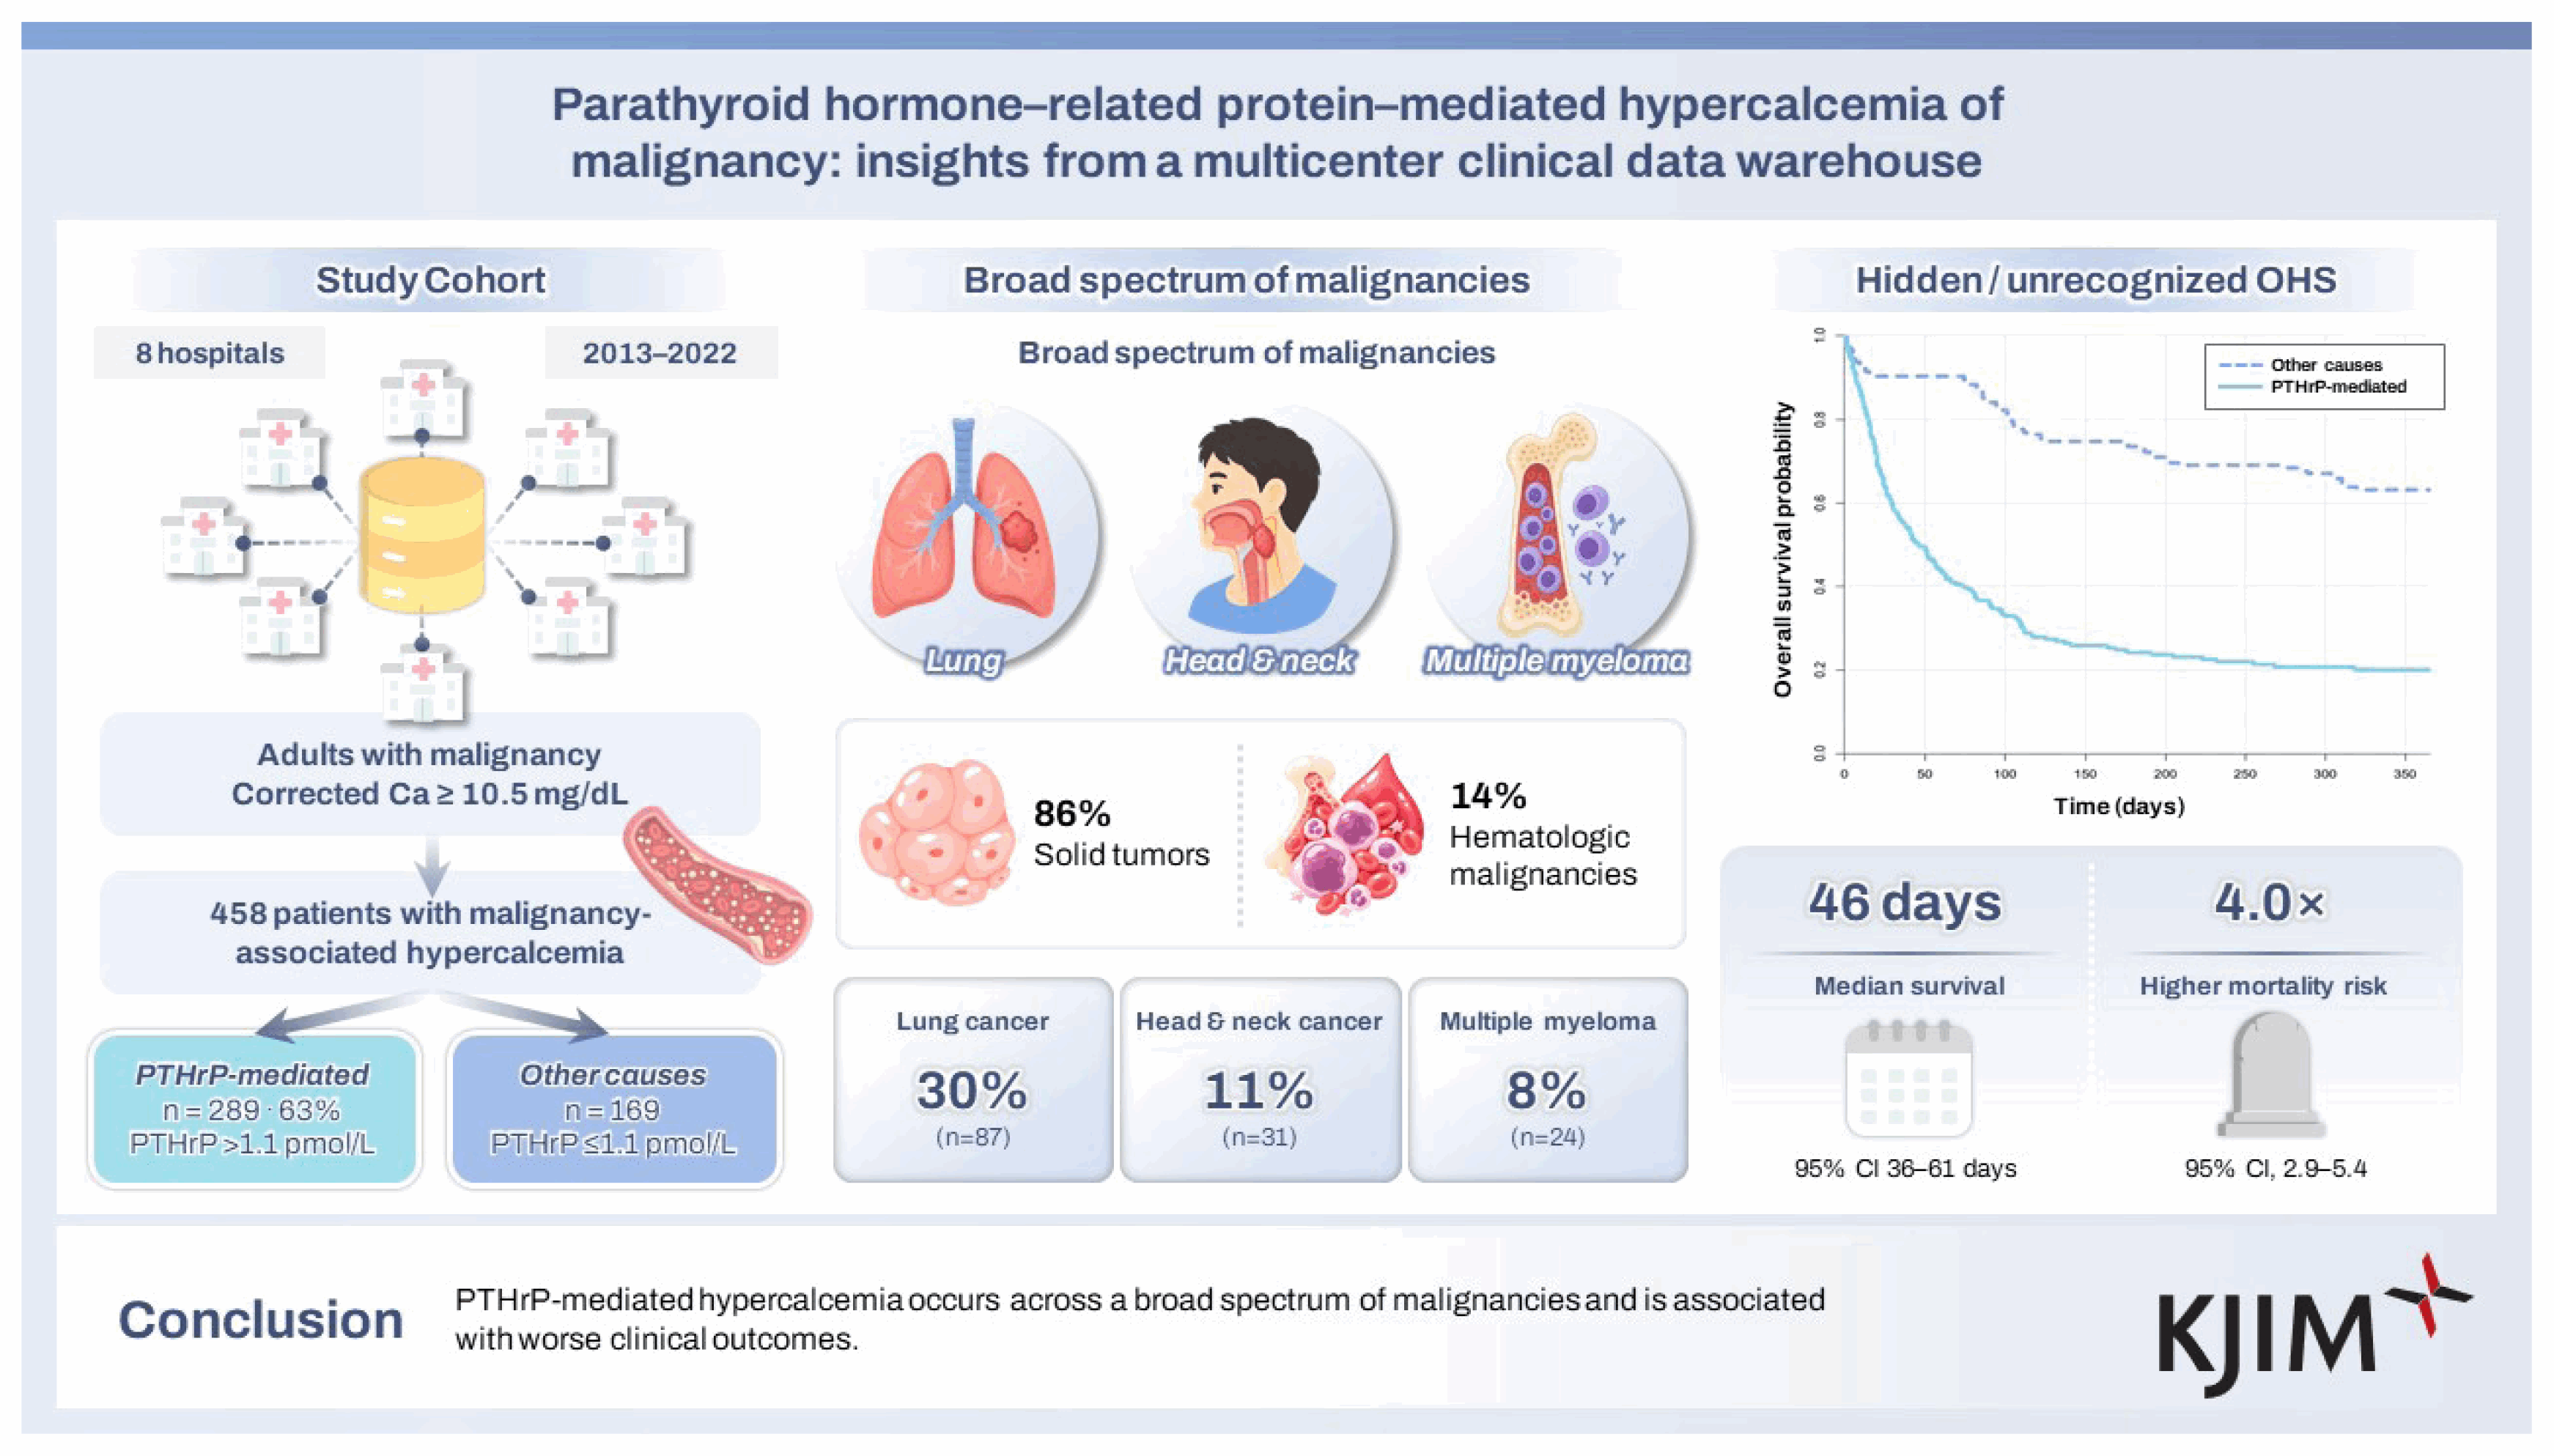
Table 1
| Variables | PTHrP-mediated (n = 289) | Other causes (n = 169) | p value | Reference |
|---|---|---|---|---|
| Age (yr) | 66 [59–75] | 66 [55–75] | 0.241 | - |
| Sex (male) | 207 (71.6) | 85 (50.3) | < 0.001 | - |
| CKDa) | 31 (10.7) | 37 (21.9) | 0.002 | - |
| Calcium (mg/dL) | 11.8 [11.0–13.0] | 11.2 [10.7–12.1] | < 0.001 | 8.6–10.2 |
| Corrected calcium (mg/dL)b) | 12.5 [11.7–13.9] | 11.9 [11.0–12.9] | < 0.001 | |
| Albumin (g/dL) | 3.0 [2.7–3.4] | 3.4 [2.9–4.2] | < 0.001 | 3.5–5.2 |
| Phosphorous (mg/dL)c) | 2.5–4.5 | |||
| Total cohort | 2.8 [2.3–3.5] | 3.5 [2.9–4.4] | < 0.001 | |
| Non-CKD | 2.7 [2.2–3.3] | 3.4 [2.8–4.0] | < 0.001 | |
| CKD | 4.8 [4.0–5.7] | 4.2 [3.4–4.9] | 0.052 | |
| PTH (pg/mL)c) | 15–65 | |||
| Total cohort | 4.5 [2.5–7.5] | 14.4 [5.2–50.0] | < 0.001 | |
| Non-CKD | 4.10 [2.50–6.97] | 16.40 [5.20–50.90] | < 0.001 | |
| CKD | 6.50 [4.70–12.15] | 9.0 [4.6–49.0] | 0.145 | |
| 25(OH)D (ng/mL)c) | 14.8 [8.9–23.2] | 19.5 [11.6–29.4] | 0.001 | > 30 |
| PTHrP (pmol/L) | 6.1 [3.5–11.5] | - | - | ≤ 1.1 |
Data are presented as median [interquartile range] for continuous variables and number (percentage) for categorical variables. CKD, chronic kidney disease; eGFR, estimated glomerular filtration rate; PTH, parathyroid hormone; 25(OH)D, 25-hydroxyvitamin D; PTHrP, parathyroid hormone–related protein; CKD-EPI, Chronic Kidney Disease Epidemiology Collaboration.
Table 2
Table 3
| Hazard ratio (95% confidence interval) | p value | |
|---|---|---|
| Crude | 4.6 (3.4–6.1) | < 0.001 |
| Model 1 | 4.5 (3.3–6.1) | < 0.001 |
| Model 2 | 4.1 (3.1–5.6) | < 0.001 |
| Model 3 | 4.0 (2.9–5.4) | < 0.001 |
Models were adjusted as follows: Model 1 included age and cancer type; Model 2 included age and albumin-corrected serum calcium; Model 3 included age, albumin-corrected serum calcium, and cancer type. Cancer type was categorized as solid malignancy with hematologic malignancy as the reference. Hazard ratios represent the risk of death in patients with elevated parathyroid hormone–related protein (PTHrP) compared to those without elevation.
- References
- References
REFERENCES
1. Grill V, Martin TJ. Hypercalcemia of malignancy. Rev Endocr Metab Disord 2000;1:253–263.
[Article] [PubMed]3. Mallory TB. Case records of the Massachusetts General Hospital: case 27461. N Engl J Med 1941;225:789–791.
[Article]4. Moseley JM, Kubota M, Diefenbach-Jagger H, et al. Parathyroid hormone-related protein purified from a human lung cancer cell line. Proc Natl Acad Sci U S A 1987;84:5048–5052.
[Article] [PubMed] [PMC]5. Burtis WJ, Brady TG, Orloff JJ, et al. Immunochemical characterization of circulating parathyroid hormone-related protein in patients with humoral hypercalcemia of cancer. N Engl J Med 1990;322:1106–1112.
[Article] [PubMed]6. Suva LJ, Winslow GA, Wettenhall RE, et al. A parathyroid hormone-related protein implicated in malignant hypercalcemia: cloning and expression. Science 1987;237:893–896.
[Article] [PubMed]7. Stewart AF. Clinical practice. Hypercalcemia associated with cancer. N Engl J Med 2005;352:373–379.
[Article] [PubMed]8. Lai NK, Martinez D. Physiological roles of parathyroid hormone-related protein. Acta Biomed 2019;90:510–516.
[PubMed] [PMC]9. Wysolmerski JJ. Parathyroid hormone-related protein: an update. J Clin Endocrinol Metab 2012;97:2947–2956.
[Article] [PubMed] [PMC]10. Guise TA, Wysolmerski JJ. Cancer-associated hypercalcemia. N Engl J Med 2022;386:1443–1451.
[Article] [PubMed]11. Lum G. Falsely elevated parathyroid hormone-related protein (PTH-RP) in a patient with hypercalcemia and renal failure. Lab Med 2011;42:726–728.
[Article]12. Mundy GR, Edwards JR. PTH-related peptide (PTHrP) in hypercalcemia. J Am Soc Nephrol 2008;19:672–675.
[Article] [PubMed]13. Manisterski M, Golan M, Amir S, Weisman Y, Mabjeesh NJ. Hypoxia induces PTHrP gene transcription in human cancer cells through the HIF-2α. Cell Cycle 2010;9:3723–3729.
[Article] [PubMed]14. Guise TA, Yin JJ, Thomas RJ, et al. Parathyroid hormone-related protein (PTHrP)-(1139) isoform is efficiently secreted in vitro and enhances breast cancer metastasis to bone in vivo. Bone 2002;30:670–676.
[Article] [PubMed]15. Fiaschi-Taesch NM, Stewart AF. Minireview: parathyroid hormone-related protein as an intracrine factor--trafficking mechanisms and functional consequences. Endocrinology 2003;144:407–411.
[Article] [PubMed]16. Dunbar ME, Wysolmerski JJ, Broadus AE. Parathyroid hormone-related protein: from hypercalcemia of malignancy to developmental regulatory molecule. Am J Med Sci 1996;312:287–294.
[Article] [PubMed]17. Rizzoli R, Feyen JH, Grau G, Wohlwend A, Sappino AP, Bonjour JP. Regulation of parathyroid hormone-related protein production in a human lung squamous cell carcinoma line. J Endocrinol 1994;143:333–341.
[Article] [PubMed]18. Clines GA. Mechanisms and treatment of hypercalcemia of malignancy. Curr Opin Endocrinol Diabetes Obes 2011;18:339–346.
[Article] [PubMed]19. Donovan PJ, Achong N, Griffin K, Galligan J, Pretorius CJ, McLeod DS. PTHrP-mediated hypercalcemia: causes and survival in 138 patients. J Clin Endocrinol Metab 2015;100:2024–2029.
[Article] [PubMed]20. Jin J, Chung JO, Chung MY, Cho DH, Chung DJ. Clinical characteristics, causes and survival in 115 cancer patients with parathyroid hormone related protein-mediated hypercalcemia. J Bone Metab 2017;24:249–255.
[Article] [PubMed] [PMC]21. Sharma A, Seow JJW, Dutertre CA, et al. Onco-fetal reprogramming of endothelial cells drives immunosuppressive macrophages in hepatocellular carcinoma. Cell 2020;183:377–394e21.
[Article] [PubMed] [PMC]22. Terpos E, Ntanasis-Stathopoulos I, Dimopoulos MA. Myeloma bone disease: from biology findings to treatment approaches. Blood 2019;133:1534–1539.
[Article] [PubMed]23. Abe M, Hiura K, Wilde J, et al. Role for macrophage inflammatory protein (MIP)-1α and MIP-1β in the development of osteolytic lesions in multiple myeloma. Blood 2002;100:2195–2202.
[Article] [PubMed]24. Shimizu H, Monden T, Tomotsune T, et al. A case of myeloma with hypercalcemia caused by high serum concentrations of both parathyroid hormone-related peptide (PTHrP) and macrophage inflammatory protein-1α (MIP-1α). Intern Med 2011;50:2993–2996.
[Article] [PubMed]25. Cafforio P, Savonarola A, Stucci S, et al. PTHrP produced by myeloma plasma cells regulates their survival and pro-osteoclast activity for bone disease progression. J Bone Miner Res 2014;29:55–66.
[Article] [PubMed]




