




A 70-year-old man presented to the emergency department with dizziness and dyspnea for 2 days. His blood pressure was 96/55 mmHg and heart rate was 31 beats per minute (bpm). He had previously undergone two radiofrequency catheter ablations for paroxysmal atrial fibrillation 4 and 6 years earlier and had remained asymptomatic without anti-arrhythmic therapy.
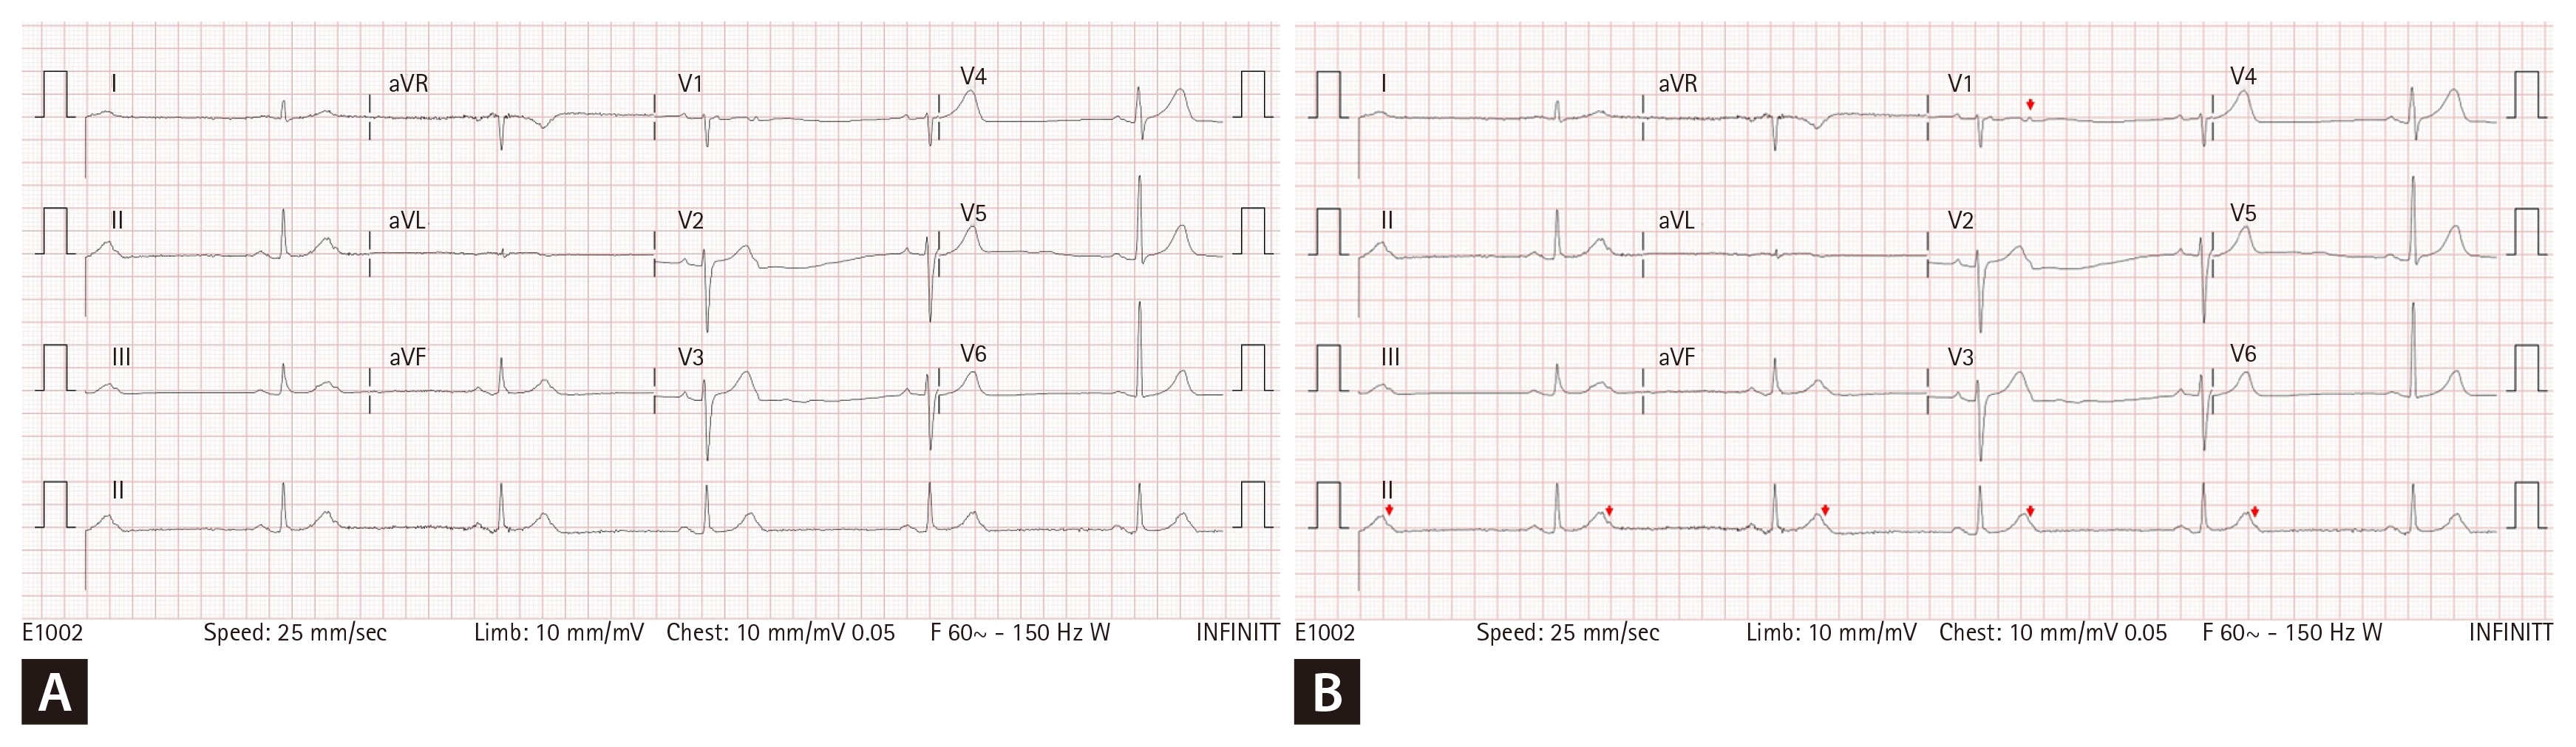
A 12-lead electrocardiogram (ECG) showed marked bradycardia with a ventricular rate of 32 bpm (Fig. 1A). The tracing initially suggested sinus bradycardia. However, careful review of the ECG revealed small deflections embedded in the terminal portion of each T wave, consistent with premature atrial contractions (PACs) (Fig. 1B). These PACs occurred in a bigeminal pattern with a coupling interval of approximately 600 ms and were not conducted to the ventricle because they fell within the effective refractory period of the atrioventricular (AV) node. The blocked PACs reset the sinus node, resulting in pauses and a markedly reduced ventricular rate.
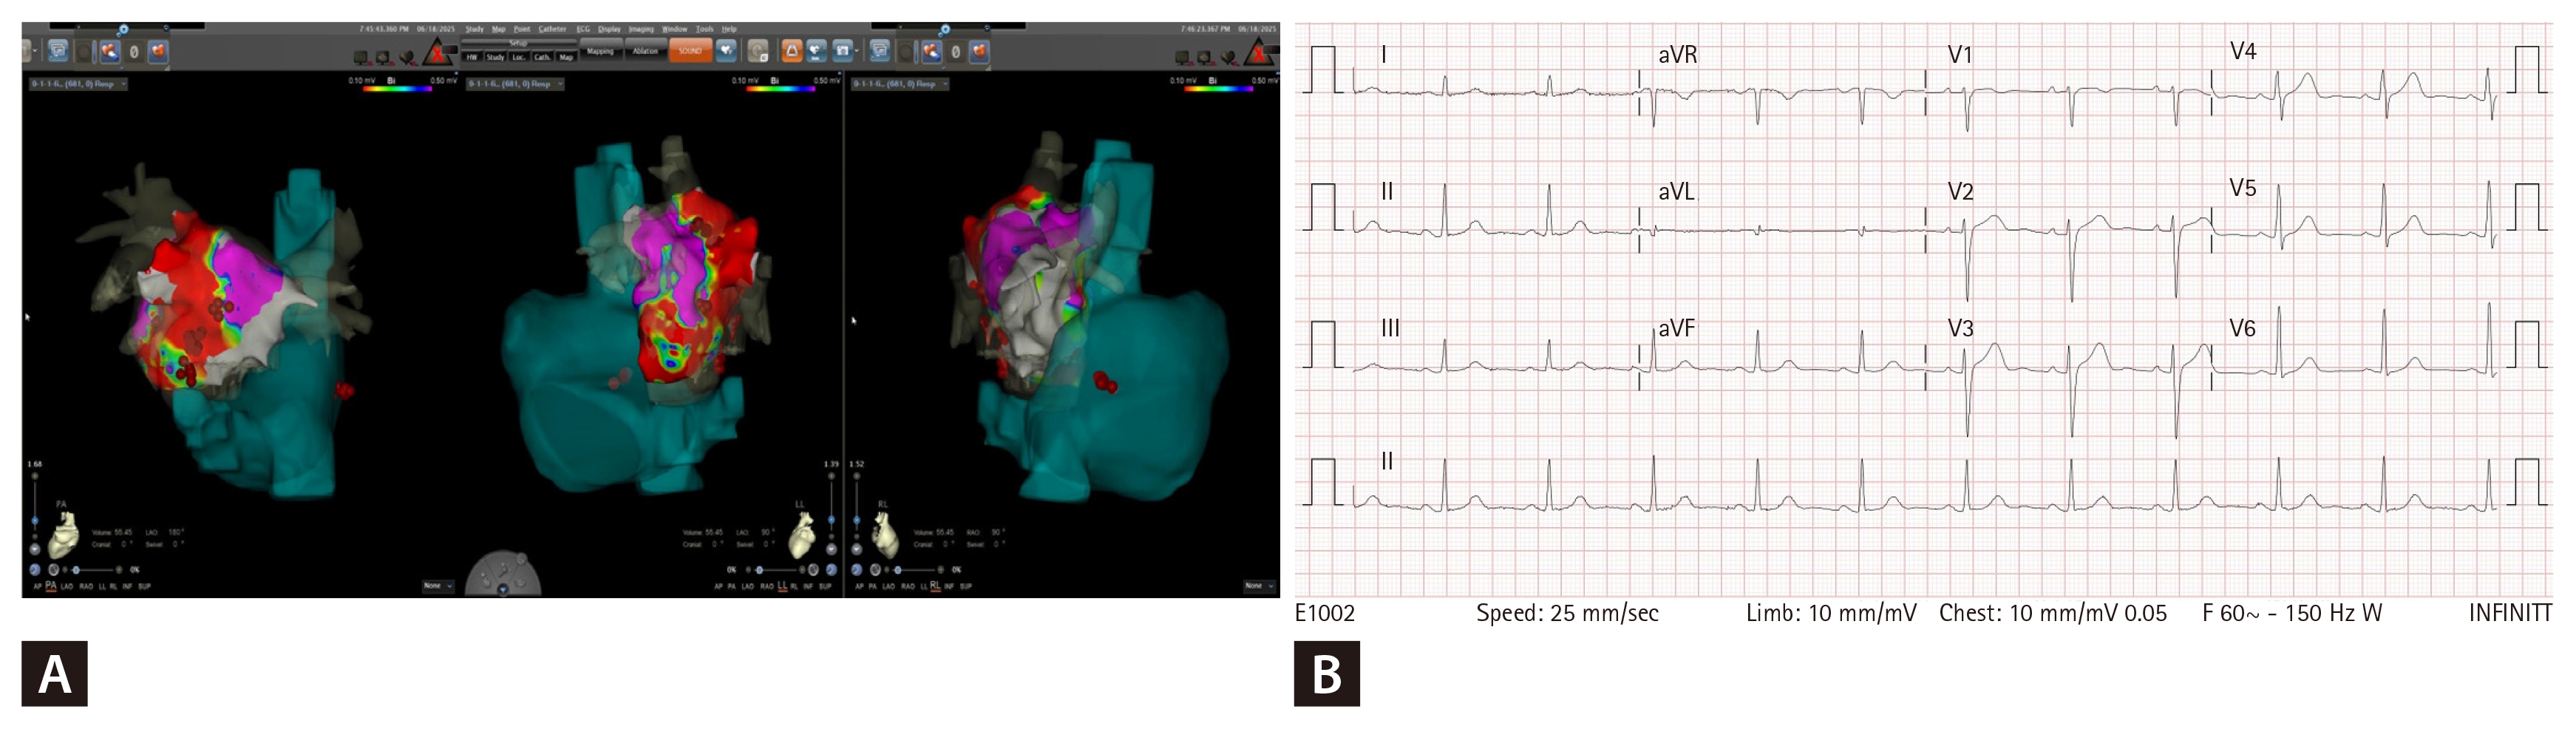
Thus, the symptomatic bradycardia was not caused by intrinsic sinus node dysfunction or AV conduction disease but by non-conducted PACs. An electrophysiologic study with three-dimensional mapping (CARTO3) was performed. Multiple PAC foci were identified in the left atrium and right atrium, and radiofrequency catheter ablation was performed (Fig. 2A). After elimination of the PACs, normal sinus rhythm with 1:1 AV conduction was restored (Fig. 2B). The patient’s symptoms resolved completely, and he was discharged without the need for pacemaker implantation.
Blocked PACs are an uncommon but reversible cause of symptomatic bradycardia and can be effectively treated with catheter ablation [1]. Recognition of this mechanism is essential to avoid unnecessary pacemaker implantation.


 PDF Links
 PubReader
 ePub Link
 XML Download
 Full text via DOI
 Download Citation
 Print





